

Health-Based Exposure Limits for Cleaning Validation
Health-based exposure limits (HBELs) provide the toxicological basis for determining how much unintended exposure to a pharmaceutical substance can be considered acceptable. In cleaning validation, the HBEL is used to establish a patient-safety-based starting point for controlling carryover from a previously manufactured product into a subsequently manufactured product.
An HBEL is not itself a swab limit, surface limit, or rinse-sample acceptance criterion. It is normally expressed as an allowable daily exposure, such as milligrams or micrograms per person per day. That toxicological value must subsequently be translated through the manufacturing scenario into a maximum allowable carryover and then into measurable cleaning-validation acceptance criteria.
This distinction is central to a scientifically defensible cleaning program. Toxicology establishes an acceptable exposure; manufacturing and equipment information determine how that exposure translates into allowable carryover; sampling and analytical procedures determine whether the resulting residue limit can actually be measured. The broader relationship is addressed in Cleaning Validation Program Strategy, Scope, and Lifecycle.
Regulatory and Scientific Context
U.S. drug CGMP regulations do not prescribe a universal PDE, ADE, or HBEL equation for cleaning validation. 21 CFR 211.67 — Equipment Cleaning and Maintenance instead requires equipment to be cleaned and maintained at appropriate intervals to prevent contamination that could alter drug-product safety, identity, strength, quality, or purity. FDA further states that manufacturers using nondedicated equipment for potent, cytotoxic, mutagenic, or highly pharmacologically active products should identify the cross-contamination risks and establish controls, including adequate cleaning and cleaning validation.
For API manufacturing, FDA’s ICH Q7 guidance explicitly links cleaning-validation residue limits to potency, toxicity, stability, solubility, and difficulty of cleaning. ICH Q7 also distinguishes highly sensitizing substances from other highly active or toxic materials and recognizes validated cleaning, inactivation, containment, and—in appropriate cases—dedicated production areas as elements of the control strategy.
A particularly detailed scientific framework is provided by the EMA guideline on HBELs for shared facilities. It calls for a structured review of available pharmacological and toxicological information and derivation of a safe threshold such as a permitted daily exposure (PDE). The guideline specifically states that these health-based values can support carryover limits used in cleaning validation.
Current FDA inspection materials also demonstrate the practical importance of toxicologically derived limits. FDA’s 2026 compliance program for certain CDER-regulated biological-product prelicense and preapproval inspections instructs investigators evaluating highly potent or toxic products to assess use of toxicologically derived ADE values for carryover limits on shared product-contact equipment and the adequacy of analytical methods used for cleaning validation. This inspection program has a specific biologics PLI/PAI scope and should not be presented as a universal regulation, but it illustrates the current FDA risk-based approach to potent-product cross-contamination.
HBEL, PDE, and ADE Terminology
HBEL — Health-Based Exposure Limit is the broad concept: a substance-specific exposure level derived from toxicological and pharmacological information and intended to protect against adverse health effects.
PDE — Permitted Daily Exposure is the terminology used in the EMA shared-facilities guideline and in several ICH safety guidances. It expresses the quantity of a substance that can be taken each day without an appreciable health risk based on the available scientific evidence.
ADE — Acceptable Daily Exposure is terminology frequently used in pharmaceutical toxicology and cross-contamination risk assessment for essentially the same purpose. The EMA HBEL guideline expressly notes that PDE and ADE are effectively synonymous, and FDA materials also use ADE terminology when discussing highly potent or toxic products.
The terminology should remain consistent with the approved toxicological assessment used by the organization. There is little value in converting a professionally derived ADE into a separately labeled PDE merely for terminology. What matters is whether the assessment is compound-specific, scientifically justified, adequately documented, appropriately conservative, and suitable for the intended cross-contamination decision.
What the HBEL Represents
An HBEL represents an acceptable exposure, not an acceptable amount of residue left on a piece of equipment. This distinction prevents a common cleaning-validation error: directly comparing an HBEL expressed in µg/day with a swab result expressed in µg/cm².
The HBEL becomes useful to cleaning validation only after the manufacturing exposure scenario is considered. The amount that could remain on shared equipment depends on factors such as the subsequent product’s daily dose, applicable batch size, equipment train, shared product-contact surface area, and assumptions used in the approved carryover calculation.
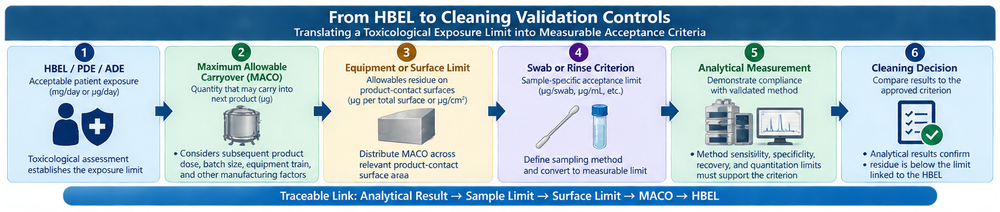
The resulting relationship is: Toxicological evidence → HBEL/PDE/ADE → allowable carryover → equipment or surface limit → swab/rinse criterion → analytical result
Each conversion represents a separate technical step and should be traceable.
Toxicological Assessment Begins with Hazard Identification
Derivation of an HBEL should begin with a comprehensive evaluation of available data rather than selection of one convenient toxicity study. The objective is to identify the effects that could occur if a patient were unintentionally exposed to the contaminating substance.
The EMA HBEL framework calls for review of available human and animal evidence, including nonclinical pharmacodynamic information, repeated-dose toxicity studies, genotoxicity, carcinogenicity, reproductive and developmental toxicity, clinical pharmacology, therapeutic effects, and adverse clinical effects. Data gaps should be identified and evaluated for their potential impact on the reliability of the exposure limit.
Other information may also be relevant depending on the compound, including mechanism of action, therapeutic class, bioavailability, target-organ toxicity, immunotoxicity, sensitization, pharmacokinetics, metabolites, reversibility of effects, population susceptibility, and clinical experience.
The objective is not simply to collect toxicity values. The assessment should determine which findings are relevant to unintended exposure of patients to a cross-contaminant.
Critical Effect and Point of Departure
After the toxicological database has been evaluated, the assessor identifies the critical effect—the adverse or pharmacological effect most relevant to establishing a protective exposure level.
A point of departure (POD) is then selected from the data supporting that effect. Depending on the data set, the POD may be a no-observed-adverse-effect level (NOAEL), lowest-observed-adverse-effect level (LOAEL), benchmark dose, clinical pharmacological dose, or another scientifically justified value.
The EMA methodology generally favors a NOAEL associated with the critical effect. Where no suitable NOAEL exists, a LOAEL can be used with an appropriate additional adjustment. Benchmark-dose methods or other scientifically justified approaches are also acceptable.
The lowest numerical dose in the entire toxicological database should not automatically be selected. The assessor must determine whether the effect is biologically relevant, adverse, applicable to humans, associated with the route and duration of interest, and supported by an adequate study.
Human Clinical and Pharmacological Data
Human information can be especially important for pharmaceutical substances because therapeutic and adverse pharmacological effects may occur at exposure levels below those producing conventional toxicity in laboratory animals.
The HBEL assessment should therefore consider therapeutic dose, minimum pharmacologically active dose where known, clinical adverse effects, dose-response relationships, target population, and unintended pharmacodynamic effects that could occur if the substance contaminates another medicinal product.
The EMA HBEL guideline specifically recognizes good-quality human clinical evidence as highly relevant. Where the critical effect is derived directly from human pharmacological or toxicological data, rigid application of the conventional animal-derived PDE equation may be inappropriate; a substance-specific evaluation of the human evidence may provide the stronger scientific basis.
This is one reason HBEL derivation should not be treated as a spreadsheet exercise. Selection and interpretation of the toxicological endpoint can have a greater effect on the final limit than the arithmetic used afterward.
Deriving a PDE or ADE
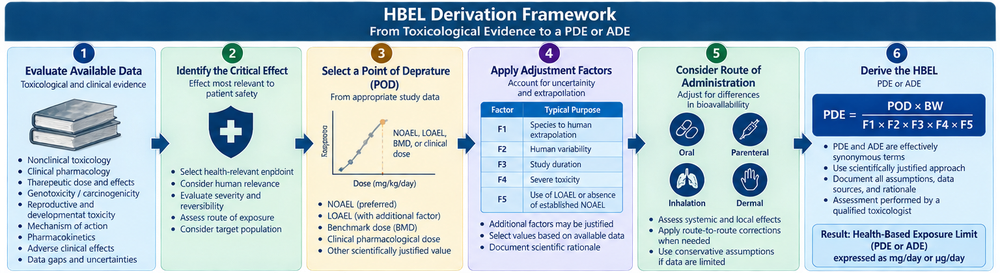
A commonly used PDE methodology begins with a NOAEL or other justified point of departure and applies adjustment factors to account for uncertainty and extrapolation.
Conceptually: PDE = Point of Departure × Body-Weight Adjustment ÷ (F1 × F2 × F3 × F4 × F5)
The equation originates from established PDE methodologies such as ICH Q3C and is incorporated into the EMA shared-facilities HBEL framework. Alternative approaches are acceptable when scientifically justified.
The equation should therefore be viewed as a toxicological framework rather than a mandatory cleaning-validation formula. The quality of the resulting HBEL depends primarily on appropriate selection of the critical effect, point of departure, adjustment factors, route assumptions, and underlying data.
Adjustment and Uncertainty Factors
Adjustment factors account for uncertainty between the experimental or clinical evidence and the exposure level considered adequately protective for the intended population. They should not be selected mechanically. Within the conventional PDE methodology:
- F1 addresses extrapolation between species when animal data are used.
- F2 addresses variability among humans.
- F3 addresses limitations associated with study duration.
- F4 addresses serious or severe toxicity where additional conservatism is warranted.
- F5 can address use of a LOAEL or LOEL when an appropriate no-effect level has not been established.
The EMA guideline permits additional modifying factors when important residual uncertainty remains, such as significant gaps in reproductive or developmental toxicity information, provided their use is scientifically justified. It also allows justified departures from default factors when the available evidence supports them.
Applying larger factors does not automatically make an HBEL scientifically better. Excessive or duplicated adjustment can produce an unrealistically restrictive limit without increasing patient protection proportionately. Conversely, unjustifiably reducing adjustment factors can produce a limit that does not adequately account for uncertainty.
Each factor should therefore have a documented rationale tied to the actual evidence.
Data Quality and Weight of Evidence
The reliability of an HBEL depends on the quality of the underlying data. A precise-looking numerical result does not compensate for incomplete literature searches, poorly characterized studies, incorrect dose interpretation, or omission of important clinical effects.
The toxicological assessment should identify the principal sources reviewed, evaluate pivotal studies for quality and relevance, distinguish original data from secondary summaries, and document important uncertainties. The EMA guideline specifically calls for a comprehensive literature search, review of pivotal animal and human studies, justification of critical endpoints and selected dose, and documented rationale for the adjustment factors used.
Where published information conflicts, the report should explain how the evidence was weighed. Where data are incomplete, the limitation should be explicit and addressed through additional adjustment, read-across, conservative categorization, TTC-based methods where scientifically appropriate, or another justified strategy.
An HBEL should not be copied from an internet database, supplier certificate, safety-data sheet, occupational exposure limit, or another manufacturer’s assessment without determining whether the source, route, endpoints, assumptions, and intended use are appropriate.
Role of the Toxicologist
HBEL derivation requires professional toxicological judgment. The assessor should have sufficient education, training, and experience to evaluate nonclinical toxicology, clinical pharmacology, human health relevance, dose-response relationships, data quality, route effects, and uncertainty.
The toxicologist’s role is broader than inserting a NOAEL into an equation. The assessor must identify relevant hazards, determine the critical effect, select the appropriate point of departure, evaluate human relevance, justify adjustment factors, assess route differences, evaluate unusual hazards, and conclude whether a threshold-based exposure limit can be established at all.
The EMA reporting framework calls for expert review, documentation of pivotal references, rationale for the selected critical effect and dose, justification of adjustment factors, expert identification and signature, and a summary of the expert’s qualifications.
Quality or Validation should review the resulting assessment for its intended GMP application, but technical approval of the toxicological derivation should remain with personnel qualified to make the underlying health-risk judgments.
Route of Administration Matters
The route by which the subsequent product is administered can affect systemic exposure to a carried-over residue. An orally derived HBEL may not automatically be appropriate when the possible contaminating exposure is inhalational, parenteral, ophthalmic, or through another route with substantially different bioavailability.
The EMA HBEL guideline specifically addresses route-to-route extrapolation. Where differences in bioavailability are significant, an appropriate correction may be required. If human route-specific data are unavailable and the new route could increase systemic exposure—for example, changing from oral to inhalational exposure—a conservative assumption can be appropriate. Route extrapolation should be assessed case by case.
Route assessment should consider both systemic and local effects. An exposure level protective for systemic toxicity may not necessarily address a local respiratory, ocular, dermal, or injection-site effect if that effect becomes the critical endpoint.
Genotoxic Substances and Non-Threshold Effects
Some hazards do not fit a conventional threshold-based NOAEL/PDE model. Certain genotoxic carcinogens may be treated as having no clearly discernible exposure threshold, meaning that the risk-management approach must be based on an acceptable level of risk rather than an assumed no-effect dose.
The EMA HBEL guideline recognizes TTC-based or compound-specific risk approaches for non-threshold genotoxic substances and distinguishes them from genotoxic mechanisms for which a biological threshold can be established.
The appropriate approach should be selected by the toxicologist and should be consistent with current toxicological and regulatory principles applicable to the compound. A standard PDE calculation should not be forced onto a substance when its mechanism of toxicity makes that model inappropriate.
Highly Sensitizing Materials
Highly sensitizing compounds require particular caution because very small exposures can produce severe immune-mediated reactions in susceptible individuals, and in some situations available data may not support establishment of a reliable safe exposure threshold.
For U.S. finished pharmaceuticals, penicillin products are subject to specific segregation requirements under 21 CFR 211.42(d), and FDA emphasizes the risk of hypersensitivity and potentially serious allergic reactions from cross-contamination.
ICH Q7 similarly expects dedicated production areas for highly sensitizing materials such as penicillins and cephalosporins. For materials with high pharmacological activity or toxicity, a risk-based strategy may include validated cleaning or inactivation, containment, or dedicated production areas depending on the ability of the controls to manage the risk.
An extremely low calculated HBEL should therefore not automatically be interpreted as evidence that unrestricted shared manufacture is acceptable. The broader question is whether the facility, process, containment, cleaning system, analytical method, and procedural controls can reliably maintain exposure below the required level.
Highly Potent and Highly Toxic Products
FDA does not impose a general requirement that every potent, cytotoxic, mutagenic, or highly pharmacologically active drug use dedicated equipment. FDA instead expects manufacturers to identify the cross-contamination hazard and establish controls adequate to eliminate the risk, including cleaning and cleaning validation where shared equipment is used.
The feasibility of shared equipment should therefore be evaluated after the toxicological limit is known. If the HBEL produces a carryover limit below what the cleaning process can reproducibly achieve or below what the analytical procedure can reliably measure, the appropriate response is not to weaken the HBEL.
Potential controls can include improved cleaning, additional containment, campaign restrictions, disposable product-contact components, dedicated equipment, or broader segregation. FDA’s current inspection instructions for certain highly potent or toxic biological products specifically call for evaluating dedicated or disposable equipment where the predetermined carryover limit cannot be achieved.
Biopharmaceuticals, Peptides, and Macromolecules
Large therapeutic molecules can require a different assessment from conventional small-molecule APIs. Proteins and peptides may denature, hydrolyze, or otherwise become pharmacologically inactive when exposed to extreme pH, heat, oxidants, or other cleaning conditions.
The EMA HBEL guideline recognizes that cleaning conditions can degrade therapeutic macromolecules and peptides and that, where validated inactivation is relevant, use of the HBEL for the intact active product may not always be necessary. Other potential cross-contamination pathways still require case-specific evaluation.
Claims of degradation or inactivation should be supported by data. A cleaning agent should not simply be assumed to destroy biological activity because it is chemically aggressive.
HBEL and Worst-Case Product Selection
The HBEL is an important input to Worst-Case Product, Equipment, and Cleaning Condition Selection, but it should not be used as the only ranking criterion.
A product with the lowest HBEL creates a highly restrictive patient-safety limit but may be readily removed from the equipment. Another product may have a higher HBEL but be considerably more difficult to clean because of poor solubility, formulation characteristics, residue aging, surface interaction, or equipment geometry.
The cleaning-validation program may therefore require different representatives for toxicological worst case and cleanability worst case. The objective is to define a set of representative challenges that collectively covers both consequence of carryover and difficulty of residue removal.
Translating the HBEL into Maximum Allowable Carryover
The next step is converting the daily exposure limit into the quantity of the previous product that may potentially carry into the next product without exceeding the allowable exposure.
Maximum Allowable Carryover (MACO) and Residue Limit Calculations addresses this calculation in detail. Depending on the approved calculation model, relevant inputs can include:
- HBEL/PDE/ADE of the previous product;
- maximum daily dose of the subsequent product;
- minimum applicable subsequent-product batch size;
- shared equipment surface area;
- manufacturing or equipment grouping;
- other justified exposure assumptions.
This produces a mass-based carryover limit. The HBEL itself should remain unchanged during this conversion; manufacturing variables change the allowable mass of residue, not the underlying toxicological exposure considered acceptable.
From MACO to Measurable Cleaning Limits
A MACO value represents the allowable quantity of residue associated with the shared manufacturing scenario. It still must be translated into limits that can be applied to actual cleaning-validation samples.
Cleaning Validation Acceptance Criteria and Surface, Swab, and Rinse Limits should define how the allowable carryover is distributed across applicable product-contact surface area and converted into criteria such as µg/cm², µg/swab, µg/mL of rinse, or another appropriate measurement.
The conversion should be transparent enough that the final analytical result can be traced back to its patient-safety basis:
Analytical result → sample limit → surface/equipment limit → MACO → HBEL
This reverse traceability is particularly useful during investigations, regulatory inspections, and assessment of changes to toxicological values or equipment configuration.
Analytical Capability Must Support the HBEL-Derived Limit
A scientifically strong HBEL is of limited operational value if the resulting cleaning criterion cannot be measured reliably.
Analytical Sensitivity and Quantitation Limits in Cleaning Validation should evaluate whether the applicable LOQ and complete analytical procedure can support the concentration represented by the cleaning acceptance limit. Analytical Method Validation for Cleaning Residue Testing should demonstrate the required specificity or selectivity, accuracy, precision, range, matrix control, recovery, and quantitative capability.
The analytical method should not dictate the toxicological limit. If the HBEL-derived criterion is below the reliable capability of the current procedure, the appropriate response is to assess a more capable analytical method, alternative sampling strategy, conservative nonspecific method where justified, improved cleaning, containment, or equipment dedication.
Raising the cleaning limit simply because the laboratory cannot measure the scientifically justified criterion reverses the correct risk logic.
HBELs and Cleaning Validation Acceptance Decisions
Once translated into an approved cleaning acceptance criterion, the HBEL supports evaluation of swab, rinse, or other analytical results during cleaning validation and routine verification.
The cleaning result is not interpreted directly against the HBEL in mg/day. It is compared with the applicable sample-specific criterion that has been mathematically linked to the HBEL through the approved carryover methodology.
This separation should remain clear in validation documentation. The toxicological report establishes the health-based exposure limit; the residue-limit calculation establishes the manufacturing carryover limit; the sampling strategy establishes where and how residue is measured; and the analytical procedure generates the result used for the final cleaning decision.
HBEL Documentation
An HBEL assessment should be sufficiently detailed that another qualified reviewer can understand how the final value was derived.
The toxicological report should normally document:
- substance identity and relevant forms;
- intended purpose of the assessment;
- literature-search strategy;
- pharmacological and toxicological data reviewed;
- critical effects identified;
- selected point of departure;
- pivotal studies and original references;
- human clinical information;
- route-of-administration assessment;
- adjustment factors and rationale;
- special hazards such as genotoxicity or sensitization;
- significant data gaps and uncertainties;
- calculation or alternative derivation method;
- final HBEL/PDE/ADE;
- expert identity, qualifications, approval, and assessment date.
The EMA guideline specifically emphasizes traceability to original pivotal references, evaluation of study quality, justification of the critical endpoint and adjustment factors, and an executive summary suitable for GMP review.
The cleaning-validation package should reference the approved toxicological assessment rather than duplicate the entire toxicology report.
Supplier-Provided HBELs
A supplier-provided HBEL can be useful, but responsibility for the cleaning-control decision remains with the manufacturer relying on the value.
The assessment should therefore confirm that the substance identity is correct, the report is current, the data set is adequate, the derivation is transparent, the route and intended use are applicable, the toxicologist is appropriately qualified, and the final value is suitable for the site’s manufacturing scenario.
A one-page certificate containing only an ADE number without critical effect, point of departure, adjustment factors, references, and toxicological rationale provides weak support for a GMP cleaning-limit decision.
Where the supplier’s derivation cannot be adequately evaluated, an independent or internally controlled toxicological assessment may be warranted.
HBEL Lifecycle Management
HBELs should not be treated as permanent master-data values that are never revisited. The toxicological assessment represents the scientific knowledge available at a particular time.
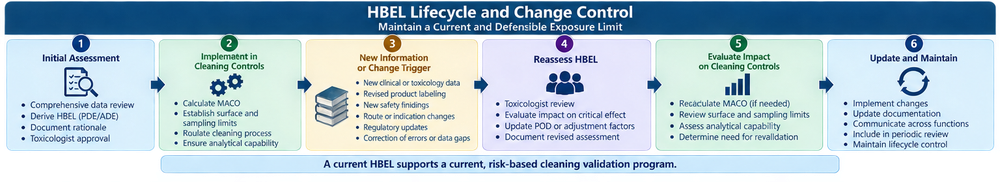
Reassessment should be considered when significant new information becomes available, including:
- new clinical safety information;
- new toxicology studies;
- revised product labeling;
- new reproductive or developmental toxicity information;
- new carcinogenicity or genotoxicity findings;
- changes in therapeutic indication or patient population;
- significant route-of-administration changes;
- new mechanistic information;
- regulatory reassessment;
- correction of errors or significant data gaps in the original report.
FDA’s risk-based approach to highly potent or toxic products likewise emphasizes updating cross-contamination risk assessments when new products or new toxicological information changes the understood hazard.
Impact of an HBEL Revision
A revised HBEL should trigger assessment of the downstream cleaning controls rather than merely replacement of one number in a database.
If the new HBEL is lower, the existing MACO, surface limits, swab and rinse criteria, analytical LOQ, worst-case rankings, and prior cleaning-validation results should be evaluated. The existing cleaning process may still remain acceptable if historical results are comfortably below the new limit, but that conclusion should be demonstrated.
If the HBEL increases, the organization is not automatically required to relax established cleaning criteria. Existing tighter limits can be retained when they remain achievable and operationally appropriate.
Cleaning Validation Change Control and Revalidation Triggers should determine whether the revision requires documentation only, recalculation of limits, analytical reassessment, targeted verification, or cleaning revalidation.
Periodic Review
The cleaning-validation periodic review should confirm that the HBEL values supporting the program remain current and that toxicological revisions have been evaluated appropriately.
Cleaning Validation Periodic Review and Continued Verification should consider newly introduced products, revised HBEL reports, changes in manufacturing sequence, altered equipment sharing, changed analytical capability, deviations, and any changes that affect the assumptions used to convert exposure limits into operational cleaning criteria.
The review does not need to repeat the toxicological assessment itself. It should confirm that the approved toxicological assessment remains current or that an appropriate expert review process is in place.
Common Deficiencies
A common deficiency is treating HBEL, PDE, and ADE as different numerical limits that must all be independently calculated. They generally serve the same health-based risk function; terminology and methodology should follow the approved toxicological assessment.
Another weakness is calculating a PDE mechanically from the lowest available NOAEL without determining whether the study represents the critical human health effect. Other deficiencies include ignoring clinical pharmacology, failing to account for route differences, using unjustified adjustment factors, relying on outdated or secondary toxicology summaries, and failing to document important data gaps.
Cleaning-validation weaknesses include using the HBEL directly as a surface acceptance criterion, confusing HBEL with MACO, using maximum subsequent-product batch size when the approved calculation becomes more restrictive with a smaller batch, and allowing analytical capability to determine the toxicological limit.
Additional concerns include accepting supplier HBEL certificates without supporting rationale, applying one value across materially different routes without assessment, assuming that every potent substance can be safely managed in shared equipment simply because a numerical HBEL has been calculated, and failing to reassess cleaning controls after the HBEL changes.
Key Principles
A health-based exposure limit establishes a toxicologically justified level of unintended patient exposure. It does not directly establish the amount of residue permitted on equipment.
PDE and ADE are effectively synonymous concepts when used as properly derived health-based exposure limits. The terminology should remain consistent with the approved toxicological assessment rather than create unnecessary parallel calculations.
HBEL derivation requires evaluation of the full toxicological and pharmacological evidence, identification of critical effects, selection of a scientifically justified point of departure, appropriate adjustment for uncertainty, consideration of route of administration, and professional toxicological judgment.
The conventional PDE equation using adjustment factors F1 through F5 is an established methodology, not a mandatory arithmetic formula for every substance. Clinical human data, benchmark-dose methods, TTC approaches, or other methods may provide a more appropriate basis when scientifically justified.
Highly sensitizing, genotoxic, highly potent, or highly toxic substances may require additional risk controls beyond routine cleaning validation. A calculated HBEL does not by itself demonstrate that shared manufacturing is acceptable.
The HBEL should be translated into MACO and then into measurable equipment, surface, swab, or rinse limits. Sampling and analytical methods must be capable of demonstrating compliance with those derived criteria.
HBELs should remain under lifecycle control. Changes in toxicological knowledge should be assessed for their impact on MACO calculations, worst-case selection, analytical capability, cleaning-validation acceptance criteria, and the continued validated state.